Understanding your semen analysis, part 2 – what you can do about the numbers

In Understanding your semen analysis, part 1, we broke down what your male fertility test results actually mean. Now, it’s time to turn that understanding into action.

Sperm production is a continuous cycle of creation and maturation – meaning that although you produce sperm every day, a full regeneration cycle (spermatogenesis) takes roughly 70–90 days.

There’s a real opportunity to support the development of healthier sperm going forward. From diet and exercise to sleep and stress, the right changes can genuinely make a difference to your sperm health over time.

What actually improves sperm quality

Lifestyle changes to improve sperm health include:

1. Reducing heat exposure

Sperm production is sensitive to temperature. So keep your testicles cool by:

  • Avoiding saunas, hot tubs and heated car seats
  • Limiting laptop use on your lap
  • Choosing loose-fitting underwear.

2. Optimising your diet

Nutrients with antioxidant properties can help protect sperm from oxidative damage. Focus on increasing your intake of:

  • Fresh fruits and vegetables
  • Nuts, seeds and whole grains
  • Lean protein
  • Healthy fats.

3. Addressing oxidative stress

Oxidative stress is a key driver of sperm dysfunction and DNA damage. Prioritise:

  • Stopping smoking or vaping
  • Limiting alcohol consumption
  • Avoiding environmental toxins where possible

In select cases, some supplements may benefit sperm health. These should be discussed with your fertility specialist, who can advise if they are appropriate for you.

4. Maintaining a healthy weight and exercise balance

Carrying excess weight is associated with reduced sperm quality. Try to regularly engage in moderate exercise, which improves hormonal balance, reduces stress and helps with your general physical and mental wellbeing.

5. Prioritising sleep and stress management

Hormonal regulation, including testosterone needed for sperm production, relies on quality sleep and low stress – factors that are often underestimated in male fertility. Work on:

  • Getting adequate sleep (7–9 hours)
  • Managing your stress levels, particularly if you have chronic stress.

6. Reviewing your medications and medical conditions

Certain medications, including synthetic hormones like anabolic steroids, and underlying health conditions can impair sperm production. A simple review with your GP or fertility specialist is often invaluable, as it can flag issues you might not otherwise think to raise.

When should you seek help?

A fertility assessment, including a semen analysis, is worth considering if conception hasn’t occurred after:

  • 12 months (if your partner is under 35 years)
  • 6 months (if over 35 years).

Seeking an assessment earlier is also welcomed, particularly if you have any concerns based on your medical or family history. Importantly, doing so early means we can step in sooner if anything needs addressing, which often leads to better conception and pregnancy outcomes.

Moving forward, together

A semen analysis is not just a set of numbers – it’s a window into a man’s overall health and one of the most sensitive barometers of male health available. On occasion, a semen analysis can even uncover important underlying medical conditions.

At Newlife IVF, our fertility specialists take a considered approach, which includes:

  • Explaining what the results mean. Many patients arrive feeling distressed, worrying unnecessarily about their results – and in most cases, their minds can be quickly put at ease
  • Interpreting results holistically, in the context of your broader health and history
  • Focusing on modifiable factors – the things that can be changed
  • Empowering you with practical, achievable steps to help you move forward.

The technology available today is remarkable. Even in cases where no sperm is detected in the ejaculate, there’s often still a path forward (and, hopefully, a pregnancy at the end of it).

So if you have any concerns at all, please don’t hesitate to seek advice. Call us on (03) 8080 8933 or book an appointment online with one of our fertility specialists.

Understanding your semen analysis, part 1 – what the numbers really mean

Around one-third of fertility treatment patients are men dealing with a male factor issue. So if that’s you, please know there’s nothing to worry or be embarrassed about. It’s a common part of the journey, and we’re here to help you through it.

A semen analysis is one of the most informative and accessible tests we have. But for many patients, the results can feel confusing. The goal of this article is to break down what each parameter means, what it tells us about your fertility potential and, most importantly, what can be done to improve it. We work alongside a wonderful team of allied health professionals and scientists, all of whom are focused on giving you the very best possible chance of achieving a healthy pregnancy. Together, we can do a lot to improve male fertility, and success is very much within reach.

First, an important perspective

A semen analysis does not diagnose male infertility on its own.

It gives us a snapshot of sperm quantity and basic function, but it doesn’t tell the full story concerning sperm performance, DNA quality or fertilisation potential. That’s why results always need to be interpreted in context, alongside your clinical history and any female factors at play.

It’s also important to acknowledge that there’s no such thing as a ‘perfect’ semen sample. Male fertility isn’t black and white but rather a spectrum, and there’s much more to the full picture than one test result.

The key parameters explained

Sperm concentration (count)

This refers to the number of sperm present in each millilitre of semen.

Why it matters

A higher concentration increases the likelihood that sperm will reach the egg.

What it means clinically

Think of this marker as strength in numbers – the more sperm present, the greater the chance that one of them succeeds in fertilising the egg. But it’s important to remember that these numbers can fluctuate dramatically for all sorts of reasons. So it’s always worth discussing your results with your fertility specialist rather than deciphering them alone.

Motility (movement)

Motility describes how well sperm move, particularly their forward (progressive) movement, which enables them to reach the egg.

Why it matters

Sperm must travel through the reproductive tract to reach the egg, so movement matters just as much as numbers.

What it means clinically

  • Good motility is essential for natural conception
  • Reduced motility (asthenozoospermia) may impact fertilisation, even when sperm count is normal.

Motility is often more important than count in determining real-world fertility potential. After all, only one sperm is needed to fertilise an egg, but that sperm still needs to move well enough to get there.

Morphology (shape)

Morphology assesses the structural appearance of sperm – including the head, which contains the sperm’s DNA, the midpiece, which supplies the energy for movement, and the tail, which propels the sperm forward.

Why it matters

Structure influences the sperm’s ability to reach and penetrate the egg.

What it means clinically

  • Morphology is the most subjective and variable of all the semen analysis parameters, because it involves manual visual evaluation under a microscope
  • Even low morphology can still result in fertilisation, particularly with IVF techniques.

Morphology is one of the parameters patients worry about most, but it rarely provides the full fertility picture on its own. It should always be interpreted alongside the other results, not in isolation.

Vitality (live sperm)

Vitality measures the percentage of live sperm in the sample.

Why it matters

Vitality becomes especially useful when motility is low, as it helps distinguish between sperm that are alive but simply not moving (immotile) and sperm that are non-viable (dead or inactive).

Beyond the basic analysis

Standard semen analysis does not assess everything, omitting:

  • DNA fragmentation: damage to the genetic material inside the sperm head, which can affect embryo quality
  • Oxidative stress: an imbalance of harmful molecules (free radicals) that can damage sperm
  • Epigenetic changes: changes to gene activity (influenced by lifestyle choices, environment, etc.) that affect how genes work and may influence embryo development
  • Functional fertilisation capacity: whether sperm can undergo the biological changes needed to penetrate and fertilise an egg.

These factors can meaningfully influence embryo development and pregnancy outcomes. That’s why a ‘normal’ semen analysis result doesn’t guarantee fertility – and, just as importantly, why an ‘abnormal’ result doesn’t mean pregnancy is impossible.

Your numbers aren’t set in stone

Sperm production isn’t fixed – it’s dynamic. This offers a powerful opportunity to improve your sperm quality.

It takes roughly 70–90 days for sperm to develop, which means the changes you make today will take a few months before they show up in your sperm quality. So give it time – meaningful change to your sperm quality happens gradually, not overnight.

There’s a lot you can do to support this process. In Understanding your semen analysis, part 2: what you can do about the numbers, we dive into the practical, everyday changes that can help improve your results.

In the meantime, if you have any concerns at all, please don’t hesitate to seek advice from one of our fertility specialists – call (03) 8080 8933 to get in touch with our clinic.

PCOS is now PMOS – a more accurate name for a complex condition

PCOS is under-researched relative to its prevalence, which creates genuine knowledge and training gaps among healthcare providers. It’s also a complex, multisystem condition that rarely follows a textbook presentation, making diagnosis feel arbitrary and the path forward unclear.

Many of my patients arrive carrying that same frustration, alongside a tangle of unanswered questions, such as:

  • ‘Do I actually have cysts?’
  • ‘Why are my symptoms so different from what I’ve read online?’
  • ‘Why has no one explained how all of this fits together?’

If any of this sounds familiar, know that your confusion is not a reflection of you – it reflects a system that hasn’t yet caught up with the complexity of this condition. But that is changing.

In 2026, after years of research and global collaboration, PCOS was officially renamed PMOS (polyendocrine metabolic ovarian syndrome). And while that may sound like a simple change in terminology, it represents something far more significant – a long-overdue shift in how this condition is understood and how people living with it are cared for.

Why did the name need to change?

The term ‘polycystic ovary syndrome’ has always been misleading. It implies the condition is defined by cysts on the ovaries, but many people with this diagnosis don’t have ovarian cysts at all. What appear as ‘cysts’ on ultrasound are often immature follicles – not true cysts in the clinical sense.

More importantly, PMOS is not just an ovarian condition. What we now understand is that it’s a complex hormonal and metabolic syndrome affecting multiple systems throughout the body, extending well beyond the reproductive organs.

The old name unintentionally narrowed the focus to the ovaries, and patients paid the price with delayed or no diagnoses. In fact, it’s estimated that up to 70% of people with this condition don’t know they have it.1 Symptoms beyond the reproductive system, such as weight changes, insulin resistance and mood disturbances, were routinely overlooked. Some people were told they didn’t have the condition simply because their ultrasound looked normal.

This renaming isn’t cosmetic. It’s a correction of decades of misunderstanding. And for many, it will mean the difference between feeling dismissed or properly seen by your healthcare practitioner.

What PMOS actually means

PMOS may sound like a more complex term, but it is far more accurate. The new name reflects three interconnected aspects of the condition:

  • Polyendocrine – multiple hormonal systems are involved, not just the ovaries
  • Metabolic – the condition affects how your body regulates insulin, energy and weight
  • Ovarian – ovulation and reproductive function remain part of the picture.

Put simply, PMOS recognises that your symptoms are connected, not random. Irregular cycles, acne, excess hair growth, difficulty losing weight, mood changes and fertility challenges are not separate, unrelated problems. Rather, they are different expressions of the same underlying hormonal disruption.

And importantly, this is a condition we understand and manage far better today than ever before.

What this means for you

For many people, this change validates what they have felt all along – that their symptoms are real, that they are connected, and that they deserve more than piecemeal care.

You may also find that conversations with your healthcare team are approached differently. Rather than focusing primarily on your menstrual cycle or the appearance of your ovaries on ultrasound, there is likely to be greater emphasis on hormone balance, metabolic health (particularly insulin resistance) and long-term wellbeing, including cardiovascular risk and mental health.

This holistic approach is exactly what many patients have been asking for.

A question I’m often asked: ‘Will my menstrual cycle become regular again?’

In many cases, the answer is yes.

PMOS often disrupts ovulation through a combination of hormonal imbalance and insulin resistance. When we address these underlying drivers, we frequently see menstrual cycles becoming more regular, ovulation returning and symptoms improving more broadly.

That said, there is no quick fix. For most patients, meaningful and lasting improvement comes from consistent, sustainable changes built up over time – not from any single intervention.

Lifestyle as medicine

Lifestyle changes are the first-line treatment for PMOS because they directly target the two core drivers of the condition – insulin resistance and hormone dysregulation.

This doesn’t mean extremes or perfection. It means:

  • Nourishing your body with foods that stabilise blood sugar
  • Moving regularly in a way that feels sustainable, not punishing
  • Prioritising sleep and managing stress.

Even small, consistent shifts can have a meaningful impact on ovulation and menstrual cycle regularity.

When lifestyle changes aren’t enough

For some people, lifestyle changes alone won’t fully address their symptoms. This is a reflection of the condition’s complexity, not a personal failing.

Depending on your symptoms and goals, we may consider:

  • Hormonal treatments to regulate the menstrual cycle and reduce the effects of elevated androgens (responsible for symptoms like acne and excess hair growth)
  • Medications, such as metformin, to support insulin function and metabolic health
  • Ovulation induction if you’re trying to conceive a baby.

These aren’t a sign of failure or of doing something wrong. They are simply additional tools – ones that work best when built on the foundation of the lifestyle changes already discussed.

Looking after the whole of you

One of the most important shifts that comes with the PMOS reframing is that your care should extend beyond physical symptoms alone. This condition doesn’t just affect your ovaries – it affects how you feel in your body every day, and your care should reflect that.

The mental and emotional toll of living with a complex diagnosis, sometimes compounded by years of feeling unheard, deserves the same attention as your physical symptoms. So too does the impact that visible symptoms, such as acne, hair changes and weight shifts, can have on body image and self-esteem. Equally important is monitoring the long-term health risks associated with PMOS, particularly an elevated risk of type 2 diabetes and cardiovascular disease – both of which are very manageable with the right support.

What this means if you’ve been living with PMOS

If you’ve struggled with a confusing or inaccurate diagnosis, this new name is significant as it represents a fundamental shift in how the condition is understood, not just what it’s called.

Your symptoms are not random, your experience is valid, and your care should be as individual as you are.

At Newlife IVF, we approach PMOS not as a label to manage, but as an opportunity to truly understand your body and build a path forward that feels achievable.

So if you’re living with PMOS and would like expert advice about ways to improve your chances of getting pregnant, you can make an appointment with one of our fertility specialists by calling Newlife IVF on (03) 8080 8933 or by booking online via our appointments page.

Reference

  1. World Health Organisation [Internet]. Polycystic ovary syndrome. Jan 2026 [cited 2026 2 June]. Available from: https://www.who.int/news-room/fact-sheets/detail/polycystic-ovary-syndrome

The two-week wait – why some patients test early and what it means

Some people may feel uncertain or apprehensive when talking to fertility clinics about home testing. We want to assure you that at Newlife IVF, we welcome discussion about your decisions and are here to support you with information and guidance.

What a positive or negative result might mean

A positive result on a urine test can feel like an enormous relief, but it isn’t always definitive. IVF medications – particularly the hCG trigger medication – can remain in your system for up to two weeks after egg retrieval, and a test taken too soon may simply be detecting what’s left of the trigger medication rather than a true pregnancy (a false positive result).

A true positive usually reflects that your body is producing hCG because an embryo has implanted. However, only a blood test can confirm the exact level of hCG hormone and whether it’s rising as it should, and this must be performed at the right time.

A negative urine test result doesn’t necessarily mean your IVF treatment cycle hasn’t produced a pregnancy. Urine tests require higher hormone levels to detect a pregnancy, and those levels may still be too low to detect during the early stage of pregnancy. Timing is crucial – testing before 10 to 12 days post-transfer is a common cause of a false negative result. So even if your home test is negative, your blood test may still come back positive.

The risks of solely relying on urine tests

If your at-home test shows a negative result, it’s important that you still attend your scheduled blood test. Home tests have important limitations, and one of the more serious is their inability to detect early warning signs of complications that a blood test would otherwise identify.

A urine test can only confirm whether hCG is present. It can’t measure how much, or whether levels are rising as they should. This distinction matters more than it might seem. A lower-than-expected hCG level, or a rise that’s slower than anticipated, can be an early indicator of an ectopic pregnancy – a condition where the embryo implants outside the uterine cavity, most commonly in a fallopian tube.

In a healthy intrauterine pregnancy, hCG levels roughly double every 48 to 72 hours. However, with an ectopic pregnancy, levels may rise more slowly or plateau, sometimes remaining low enough to evade detection on a urine test or producing a misleadingly positive result without confirming a healthy implantation site. Relying on a home test alone could delay the timely medical care your body needs, with possible serious consequences for your health.

The pros and cons of testing early

Testing early can offer convenience and privacy, and a positive result can bring emotional reassurance during an anxious wait. For many patients, this can also feel proactive and provide a sense of control.

The drawbacks, though, are worth understanding. Urine tests are less sensitive than blood tests, so testing too soon risks a false negative that may miss an early pregnancy. Meanwhile, residual hCG from a trigger injection can produce a false positive.

Most importantly, home tests cannot measure the precise hormone levels needed to properly monitor your progress.

Our advice, if you choose to test early

Testing early is a personal choice, and we understand the emotional impetus for wanting autonomy and control over knowing the outcome of your IVF cycle. The two-week wait is hard, and wanting answers is completely natural.

If you choose to take a home urine test, waiting until at least 10 days after your embryo transfer or insemination improves the chance of accurate results. And when doing so, keep in mind that a home urine test can never replace the insights provided by a blood test. A blood test remains the gold standard – it confirms whether a pregnancy has occurred, measures exact hCG levels and assesses whether your hormone levels are rising appropriately. And when paired with an ultrasound at the right time, a blood test verifies that the pregnancy is safely located in the uterus.

Your blood test also provides us with the full picture of whether a pregnancy is viable and progressing safely. If you feel anxious, uncertain or experience unusual symptoms during this time, such as pain or bleeding, please reach out to your nursing team right away.

You don’t have to navigate this alone. Our counselling team is also here to support you through the two-week wait and beyond. Your journey matters to us, and we’re committed to guiding you through every stage of fertility treatment with care and transparency.

Supported at every step – the team behind your fertility care


Fertility treatment success depends on the doctor you choose and on the strength of the entire clinic team. It is shaped by integrated support across the clinic – from the scientists working behind the scenes, to dedicated nurses, fertility counsellors and genetic counsellors providing guided care, and the administrators, finance officers, patient support and marketing team – to ensure every part of your experience is seamless and well-coordinated.

Think of it like a symphony. A soloist may shine, but it’s the orchestra as a whole – each instrument working in harmony – that creates something truly remarkable. Fertility care is no different: the sum is greater than its parts.

In this blog, we’ll show how every part of a fertility clinic plays a vital role, explaining why looking at who your specialist partners with matters for both your treatment experience and results.

Comprehensive care close to home

Newlife IVF is a Melbourne-based fertility clinic with three convenient locations: our flagship site in Box Hill, and service centres in Clayton and East Melbourne. We also offer telehealth appointments, making it easier for individuals and couples from across Victoria – including regional and rural areas – to access world-class fertility care.

We provide the full spectrum of fertility services, from initial fertility testing and early treatment options to advanced care such as IVF, ICSI (intracytoplasmic sperm injection), preimplantation genetic testing, fertility preservation, and donor or surrogacy pathways. This breadth of services allows us to tailor care to each person’s unique circumstances, ensuring patients don’t undergo unnecessary treatment, but instead receive the most appropriate care for their needs.

Best science, as standard

Behind every successful pregnancy is a foundation of rigorous science. At Newlife IVF, we are deeply committed to upholding best scientific practice and making it accessible to all our patients.

Our state-of-the-art laboratory is led by our Scientific Director, Dr Tiki Osianlis, and is equipped with the latest technology.

For IVF, we use advanced techniques such as:

  • EmbryoScope time-lapse system to continuously monitor embryo development
  • Sequential media and EmbryoGlue as a standard to support embryo growth and transfer
  • Egg spindle visualisation during ICSI, using specialised microscopes and polarised light to select eggs with the best fertilisation potential
  • PIEZO-ICSI, offering a gentler approach to ICSI that is more suited to patients with fragile eggs.

We also partner with CooperGenomics, a global leader in reproductive genetic testing, to provide patients with access to chromosomal screening and single-gene disorder testing.

Importantly, these advanced techniques are offered at reasonable prices, in line with our belief that every patient deserves the very best scientific care, not just those who can afford to pay extra.

Highly skilled embryologists – the clinic’s ‘engine room’

If the fertility specialist is the conductor of the symphony, the embryologists are the musicians bringing the music to life. Often called the ‘engine room’ of a fertility clinic, the laboratory team plays a vital role in determining the success of treatment.

At Newlife IVF, our embryologists are heavily involved in all aspects of treatment. We know how precious eggs, sperm and embryos are to our patients, and how daunting it can feel to entrust them to someone else’s care. That’s why our embryologists maintain open lines of communication, keeping patients informed about embryo progress and answering questions along the way.

We also have a comprehensive team in place so that no embryologist is overburdened. This allows each procedure to be carried out with the care, focus and attention it deserves, and reflects our commitment to optimising embryo development and, ultimately, pregnancy success.

Safeguarding your most precious cargo

The lab environment matters more than most people realise. Even seemingly small factors, such as air quality or exposure to light, can impact embryo development.

That’s why our laboratory has been purpose-built to reduce volatile compounds and harmful blue light. We also adhere to strict quality-control protocols to ensure ideal conditions for embryo growth are maintained every day.

Equally important is safeguarding the identity and integrity of every patient’s eggs, sperm and embryos. At Newlife IVF, we use a dual-layer witnessing system, comprising:

  • RI Witness electronic platform, which tracks eggs, sperm and embryos at every stage of treatment and handling
  • Double-witnessing by our embryologists, providing an additional layer of assurance.

This gold-standard system ensures every sample is accurately tracked, securely stored and handled with the highest levels of safety and accountability.

The steady presence of fertility nurses

If fertility specialists set the direction of care, fertility nurses provide continuity. With extensive experience in fertility treatment, fertility nurses are the conduit between patients and their treating fertility specialists, translating clinical decisions into clear direction and ensuring information flows clearly in both directions. They are often the team members patients interact with most, guiding them through each stage of treatment with clarity and reassurance.

At Newlife IVF, fertility nurses oversee key elements of care, including cycle monitoring through blood tests and ultrasounds, medication education and administration support, and early pregnancy care before transition to obstetric services. Working closely with fertility specialists, they coordinate treatment plans, relay results and clinical updates, and advocate for patients’ needs. By taking time to explain treatment plans, procedures and medications in detail, our nurses help patients feel informed and confident throughout their fertility journey.

Emotional care as part of clinical care

Fertility treatment can bring uncertainty, stress and complex emotions alongside the physical treatment. That is why counselling is integrated into care at Newlife IVF, rather than treated as an optional extra.

Our experienced fertility counsellors support patients through all stages of treatment, offering tools to navigate the emotional demands of fertility care. They also play a critical role in supporting decision-making, relationship dynamics and preparation for donor conception or surrogacy pathways. The aim is to ensure patients feel emotionally prepared and empowered as their journey evolves.

Genetic insight to support informed decisions

Where genetic considerations are relevant, genetic counselling provides essential clarity and guidance. Our genetic counsellors work closely with fertility specialists to assess inherited health risks, explain inheritance patterns, and interpret genetic test results in clear, practical terms.

They support patients to understand testing options such as carrier screening and preimplantation genetic testing, while also helping them explore reproductive pathways that align with their circumstances and values. Emotional and ethical considerations are addressed alongside clinical information, ensuring decisions are made with confidence.

Coordination that reduces stress

Behind every appointment, test and treatment cycle is careful coordination. Our administration team plays a vital role in ensuring fertility care runs smoothly by managing schedules, communications and documentation so patients can focus on treatment rather than logistics.

They coordinate appointments, explain timelines and processes, assist with forms and maintain close communication with clinical teams to support continuity of care. Their work helps reduce uncertainty and ensures that patients feel informed and supported throughout their experience.

Financial clarity as part of patient-centred care

Fertility treatment represents a significant investment, and financial clarity is an important part of feeling supported. Our finance team works closely with patients to explain cost estimates, manage billing and payments, and assist with Medicare and private health insurance claims.

By breaking down financial information into clear, manageable steps and responding promptly to questions, they help minimise stress and uncertainty, allowing patients to make considered decisions about their care.

Support before the first appointment

Care at Newlife IVF begins well before treatment starts. Our patient enquiries and marketing teams help people take their first steps by providing accessible, accurate information and creating opportunities to learn more about fertility care.

From responding to initial enquiries and online forms, to developing educational resources and events, these teams ensure individuals and couples feel informed and welcomed as they begin exploring their fertility treatment options.

More than the sum of its parts

Fertility treatment is an incredibly personal journey – one that involves equal measures of science, compassion and trust. While your choice of fertility specialist is important, it is one part of a much larger picture.

At Newlife IVF, every aspect of our clinic – from our laboratory and scientific team to our nurses, fertility counsellors, donor services, genetic counsellors and administrative staff – works together to create an environment where patients feel supported, and where their eggs, sperm and embryos are given the best possible chance of success.

We believe families bring joy to life. That’s why we combine world-leading science, exceptional care and genuine compassion, as we strive to help you realise your dream of starting or growing your family.

Because in the end, fertility care is it about the whole team working in harmony, with you at the very centre.

If you’re ready to explore your options for having a baby, you can make an appointment with one of our specialists by calling (03) 8080 8933 or by booking online.

Embryo grading explained – what do those numbers and letters really mean?

Here, we break down what embryo grading really represents, how it is used in IVF laboratories, and what it means – and does not mean – for your chances of success.

What is embryo grading?

Embryo grading is a system embryologists use to describe the appearance of an embryo under the microscope at a specific moment in time. It allows us to make informed decisions about which embryos to transfer or freeze, and to communicate clearly within the laboratory team when assessing embryo development.

Importantly, embryo grading is a descriptive tool rather than a guarantee of outcome. IVF laboratories may use slightly different grading systems, which means embryo grades can vary between clinics – even clinics located within the same state – and are not always directly comparable. Understanding what grading does and does not tell us can help you feel more informed and reassured throughout your IVF journey.

Why is so much attention given to embryo grading?

It’s natural to want something tangible to hold onto during IVF, and embryo grades can feel like a clear point of reference. Much like our early educational experiences, receiving a ‘grade’ can feel like an assessment of performance. Many people assume that a higher grade means a better embryo (and therefore a higher chance of success), while a lower grade suggests the opposite.

While this interpretation is understandable, it isn’t entirely accurate. There are many factors involved in embryo development and implantation, and grading alone cannot capture them all.

Embryo grading is not a prediction tool; it is an observation tool. It tells us what an embryo looks like at a particular point in time, not whether it will implant or result in a pregnancy. Every viable embryo, regardless of grade, has the potential to result in a pregnancy.

In our many years of experience in IVF laboratories, we have seen high-grade embryos that did not implant, and lower-grade embryos that went on to become healthy babies. While grading helps us prioritise embryos for transfer or freezing at that moment, it is only one piece of a much larger picture.

When do we grade embryos?

Embryos are grown in the Newlife IVF laboratory for up to six days after fertilisation. By day five or six, embryos ideally reach the blastocyst stage, which marks a critical milestone in development.

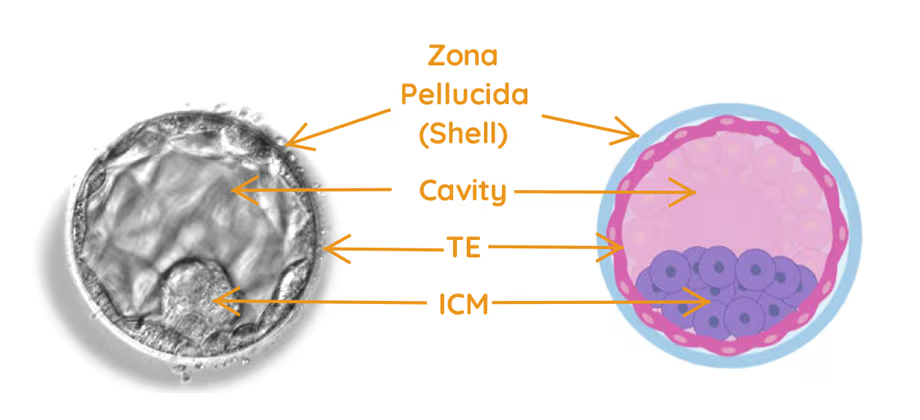
At this stage, the embryo has developed into many interacting cells, and for the first time, we can clearly identify three distinct structures:

  • Inner cell mass (ICM): A cluster of cells inside the embryo that will eventually form the baby
  • Trophectoderm (TE): The outer layer of cells that will develop into the placenta, which supports the baby during pregnancy
  • Blastocoel: A fluid-filled cavity that allows the embryo to expand.

A photographic image of a blastocyst (left) positioned next to a graphic representation of a blastocyst (right). The images show the types of cells that go on to become an embryo proper (foetus), including the zona pellucida (shell), cavity, trophectoderm cells (TE) and inner cell mass (ICM).

How does blastocyst grading work?

Blastocyst grading assesses three main features: the stage of expansion, the characteristics of the inner cell mass, and the characteristics of the trophectoderm. Each component is graded separately, as outlined below.

Expansion stage

The expansion stage refers to the size of the blastocyst and how far it has progressed in breaking free from its protective outer shell, known as the zona pellucida. As the blastocyst grows, it needs to thin and eventually break through this shell in a process called hatching.

Expansion is categorised into six stages:

  • Stage 1: Early blastocyst development, where a small fluid cavity is just beginning to form
  • Stage 2: Early expanding blastocyst, with a growing cavity but still relatively small within the shell
  • Stage 3: Expanded blastocyst, where the cavity is larger and the embryo occupies more space, but hatching has not yet begun
  • Stage 4: Fully expanded blastocyst, filling most of the shell, which has thinned significantly
  • Stage 5: Beginning to hatch, with part of the embryo emerging through the shell
  • Stage 6: Fully hatched, where the embryo has completely escaped the zona pellucida and is ready for implantation.

Inner cell mass (ICM) characteristics (A–D)

The inner cell mass is the group of cells that will go on to form the baby. It is graded from A to D based on appearance:

  • A: Many healthy cells that are tightly packed
  • B: Several cells with a slightly looser arrangement
  • C: Few cells that are scattered and less cohesive
  • D: Very few or degenerating cells (considered non-viable).

Trophectoderm characteristics (A–D)

The trophectoderm forms the placenta and is also graded from A to D:

  • A: Many cells are present, forming a strong and cohesive layer
  • B: A moderate number of cells with less uniformity
  • C: Few cells with an irregular appearance
  • D: Very few or degenerating cells (considered non-viable).

Putting it all together

When you see an embryo grade, it is simply a shorthand way of combining these three observations into a single description.

For example, a grade of 5AB means:

  • 5: The blastocyst is beginning to hatch from its outer shell
  • A: The inner cell mass has many tightly arranged cells
  • B: The trophectoderm has a reasonable number of cells forming a mostly cohesive layer (although the layer may not be uniform).

While this grading helps embryologists make informed decisions in the laboratory regarding embryo quality, it’s important to remember that no single grade can determine the outcome of an embryo.

Embryo grades are not fixed and can change over time

Embryo grading provides a snapshot in time. Embryos are dynamic and continue to grow, divide and change as they develop.

For example, an embryo graded early on day five as 2CB may look quite different later the same day, potentially developing into a 4BB embryo. This progression is entirely normal and reflects ongoing development in a viable embryo.

The same principle applies when an embryo is transferred, while others continue developing in the laboratory. An embryo transferred on day five may be graded 3BB, while its siblings reassessed later could receive a seemingly higher grade, like 5AA. This difference is often due simply to timing and additional hours of development – not because the transferred embryo was a poorer option.

At the time of transfer, the chosen embryo was assessed as the best option based on its developmental stage, appearance and timing. Because grading is so closely linked to when an embryo is observed, it is not a reliable way of comparing embryos with one another. Instead, grading is just one part of a broader decision-making process.

You can learn more about this approach in our blog, How we select embryos for transfer.

What grading can (and can’t) tell us

In general, higher embryo grades are associated with higher pregnancy rates, which is why grading remains a useful tool when deciding which embryos to transfer or freeze.

However, embryo grading is not an absolute predictor of outcome. A high-grade embryo does not guarantee a pregnancy, and a lower-grade embryo does not mean a pregnancy will not occur. In practice, we regularly see examples where a high-grade embryo, such as 6AA, does not implant, while a sibling embryo with a lower grade goes on to result in a healthy baby.

Once a pregnancy is established, the embryo’s grade is no longer relevant. It does not predict whether a pregnancy will continue, nor does it reflect the future health of the baby.

If an embryo has been transferred or frozen, it has been deemed viable and has potential. Every viable embryo, regardless of grade, has the capacity to become a baby. For patients with embryos of varying grades in storage, or those who have had a lower-grade embryo transferred, there is every reason to remain hopeful.

Looking beyond letters and numbers

Embryo grading is only one part of how we assess embryo development. In addition to visual grading, we use time-lapse imaging, key developmental milestones, embryologist expertise and AI-powered tools to observe how embryos grow and behave over time.

Together, these approaches provide a better understanding of embryo health and potential, helping us make the most informed decisions for your treatment.

Our guidance for patients

We encourage Newlife IVF patients to focus on the number of viable blastocysts rather than becoming fixated on letters and numbers. An embryo’s potential is far greater than its grade alone.

If an embryologist has transferred or frozen your embryo, the embryo has the capacity to continue developing, and this potential matters far more than a single snapshot assessment.

Interested to learn more about embryo grading or IVF?

If you would like to understand more about embryo grading or IVF treatment, be sure to listen to the embryo optimisation podcast episode. Our team at Newlife IVF is also here to support and guide you throughout your fertility journey – call us on (03) 8080 8933.

Is egg freezing right for you?

If you’d like to have a family one day, egg freezing offers a way to preserve some of your younger, healthier eggs by storing them for future use. This option can help protect your future fertility, giving you the freedom to plan pregnancy when the time feels right – without feeling rushed by your biological clock – while increasing your chances of conceiving if any challenges arise.

At Newlife IVF, we believe egg freezing should be an accessible and affordable option for all women, no matter their reasons for choosing this path.

Why do women freeze their eggs?

In some cases, egg freezing is about timing – the right time for you to have a baby may not be the right time in terms of your fertility. Whether you’re focusing on your career, furthering your education, travelling, waiting for the right partner or achieving financial stability, egg freezing offers flexibility for those who aren’t yet ready to commence trying to conceive. Freezing your eggs at a younger age, when they are more likely to be of higher quality, helps preserve your fertility by ‘pressing pause’ on the natural decline in egg quality that comes with ageing. This gives you the option to revisit your family-building goals when the timing feels right for you.

Egg freezing for medical reasons

Certain health conditions and medical treatments can affect fertility, making egg freezing a valuable option. For example, it may be recommended before treatments such as chemotherapy or radiotherapy to help preserve future reproductive options.

Additionally, women with reproductive health concerns, such as endometriosis or polycystic ovary syndrome (PCOS), may consider egg freezing as a proactive step in preserving their fertility. Endometriosis is a condition where tissue similar to the uterine lining grows outside the uterus, which can affect egg quality and reduce ovarian reserve. Similarly, PCOS, a hormonal disorder that disrupts ovulation, can lead to increased difficulties in conceiving. In these cases, freezing eggs may provide an option for future family planning, including the possibility of IVF if needed.

What is the best age to freeze your eggs?

Once you have made the decision to freeze your eggs, it’s best to get started as soon as possible – ideally in your late 20s or early 30s when you still have a reasonable number of good-quality eggs. The quantity and quality of eggs are the most important factors when going through fertility treatment.

Unfortunately, eggs collected from women over the age of 35 are not as successful when used in IVF cycles. Therefore, if you are over 35, we will typically try to collect a greater number of eggs which means that you may have to go through more egg freezing cycles. This increases the likelihood that one or more of the eggs we collect will be appropriate for IVF, should you need to go down this path in the future.

What does egg freezing involve?

This infographic outlines the various steps involved in egg freezing: obtaining a GP referral, consulting with a fertility specialist, meeting with other team members, awaiting your period before starting the medication, undergoing blood tests and scans, administering a trigger injection (to induce egg maturation), attending days surgery for egg collection, and freezing and storing eggs.

Step 1 – obtain a GP referral

You need a referral from your GP before seeing a fertility specialist to discuss egg freezing. This also allows you to access the Medicare rebate if you are eligible, e.g. where an underlying illness or medical treatment could impact your future fertility.

Step 2 – fertility specialist appointment

Your Newlife IVF fertility specialist will review your medical history, order any blood tests and ultrasounds required, and develop a personalised treatment plan based on your unique circumstances. Your specialist will also discuss with you the number of eggs they expect to be able to collect based on your age and other factors, the likely chance of pregnancy from using eggs frozen at your age, and whether multiple egg collection cycles might be beneficial for you.

Step 3 – additional appointments

You’ll have a session with one of our counsellors to ensure you feel informed and supported. We’ll arrange a finance meeting to provide a clear breakdown of all costs involved, and you’ll meet with one of our fertility nurses, who will guide you through the treatment process. Your nurse will tell you about the different medications involved in egg freezing, teach you how to self-inject the required hormonal medications at home, and let you know what to expect during the egg collection procedure at our day surgery.

Step 4 – preparing for treatment

Once your period begins (day 1), call the nursing team to inform them. On day 2, start your medication as directed to start stimulating your ovaries (see next step).

Step 5 – ovarian stimulation

In order to stimulate your ovaries to produce multiple eggs for collection, you will need to self-administer daily hormone injections over an 8–14 day period (we will show you how to do this safely and comfortably).

Step 6 – monitoring

Throughout the stimulation period, we will use ultrasound to monitor any developing follicles (which contain your eggs). This helps us determine the best time to collect your eggs.

Step 7 – egg collection

Once mature, we will collect your eggs while you are lightly sedated. Surgery takes 10–15 minutes and an average of 8–15 eggs are typically collected.

Step 8 – storage

From the eggs we collect, we will identify any mature eggs and freeze them. Your frozen eggs will be carefully stored in our quality-controlled facility until a time when you might choose to use them in the future (frozen eggs can be stored for up to ten years in Victoria).

What are the risks involved in egg freezing?

Egg freezing is considered a safe procedure. Though, like any medical intervention, it carries some small risks and side effects. These may include ovarian hyperstimulation syndrome (OHSS) as a response to stimulation medications, discomfort during egg retrieval and, in rare cases, complications such as bleeding or infection. Serious complications are uncommon.

Consulting with a fertility specialist can help you decide if egg freezing is the right option for you, along with understanding the process, risks and potential outcomes.

How many eggs do I freeze?

Our fertility specialists aim to collect the highest number of mature eggs that can be obtained safely. The ideal number varies depending on your age, ovarian reserve and your future family planning goals. Often more than one cycle of egg freezing is needed to collect enough eggs to give a good chance of a baby in the future.

While egg freezing can help preserve your younger eggs, it does not guarantee a future pregnancy or baby. Between egg collection and a successful birth, several important stages still need to occur. For example, after thawing, the eggs must be successfully fertilised using your partner’s or donor sperm to create embryos. Those embryos then need to continue developing appropriately before one is transferred to the uterus and successfully implants, ultimately leading to pregnancy and birth.

Therefore, having a higher number of frozen eggs can improve the likelihood of progressing through the stages required to achieve a future pregnancy.

How many eggs do most women get?

The number of eggs collected in one cycle varies widely. Some women collect fewer than 5 mature eggs in one cycle, while others collect 20 or more. This depends largely on age, ovarian reserve and how the ovaries respond to stimulation medication. Your fertility specialist can estimate how many eggs you may be able to obtain after assessing your ovarian reserve with a blood test and ultrasound scan.

What are the success rates for conceiving a baby using frozen eggs?

Egg freezing provides the potential for a future pregnancy, but success is not guaranteed. While over 98% of frozen eggs survive the thawing process, achieving pregnancy depends on several key IVF stages, including fertilisation, embryo development and implantation in the uterus – each with its own challenges.

The likelihood of a live birth from frozen eggs is further influenced by your age at the time of freezing and the number and quality of eggs collected. Age is the most reliable indicator of egg quality, with younger eggs generally having a higher chance of leading to a successful pregnancy. This is because the proportion of eggs with the correct number of chromosomes declines naturally with age, reducing the chance that each egg will result in a healthy pregnancy. For example:

If a woman freezes 20 eggs before the age of 35, studies show the estimated chance of having a baby from those eggs is around 80%. Freezing 40 eggs increases this likelihood to over 90%.

However, if a woman freezes 20 eggs at the age of 40, the estimated chance of having a baby from those eggs is less than 50%.

Therefore, if you are considering egg freezing, speaking with a fertility specialist earlier rather than later can help you explore your options. While each person’s fertility journey is unique, starting the conversation in your younger years typically provides more flexibility and choices for your future family planning. The natural biology of egg quality means that preserving eggs at a younger age may increase your chances of successful fertility treatment later on, should you choose that path.

The number of eggs collected in each cycle depends on a patient’s ovarian reserve and how their body responds to the medication. Because of this, egg freezing may require multiple treatment cycles to achieve an optimal number of eggs for future use.

Is it better to freeze eggs or embryos?

If you have a current partner and are considering your fertility preservation options, you may be wondering whether it is better to freeze eggs or embryos. Both are effective options, and the right choice depends on your personal circumstances, future plans and preferences.

Egg freezing preserves your eggs in an unfertilised state. This gives you the flexibility to decide in the future who you may have children with and avoids the legal and emotional complexities that can arise if your current relationship changes over time. You retain sole control over decisions regarding the future use of your frozen eggs.

Embryo freezing involves fertilising the eggs with sperm and allowing the resulting embryos to develop before freezing them. This can provide more information about the egg quality and may provide a clearer indication of your chances of a baby. For example, embryos can be graded to assess their development, giving you a clearer indication of how many viable embryos may be available for future IVF treatment. If appropriate, embryos can also undergo preimplantation genetic testing (PGT) tto screen for chromosomal abnormalities. Eggs alone cannot undergo these forms of assessment. However, in Australia, embryos created with a partner generally require the consent of both people before they can be used. If the relationship changes or ends, this sometimes prevents the future use of the frozen embryos.

It is important to discuss both options with your fertility specialist to determine the best path for you.

What does egg freezing cost?

Newlife IVF is committed to offering reasonable pricing, reflecting our belief that egg freezing should be accessible to all. While elective (non-medical) egg freezing isn’t covered by Medicare, egg freezing for medical reasons is. You can visit our fees page for a general overview of the costs involved. We recommend booking an appointment with one of our fertility specialists in Melbourne for personalised advice and a clearer understanding of the costs based on your specific circumstances.

Your timeline, your choice

Life doesn’t wait for anyone – but you can make your eggs wait for you. Be fertility ready when you’re ready.

If you need help deciding whether egg freezing is right for you, contact us to talk about your options.

How embryos develop – from egg retrieval to blastocyst

After retrieval, the egg and sperm are combined, and if fertilisation is successful, your embryo spends the first few days growing in the lab under the expert care of our team. This blog will help guide you through these early embryo development steps before transfer or freezing.

Factors affecting embryo development

Embryo development is a complex process that requires a combination of genetic, environmental and physiological factors to progress successfully. To achieve good embryo development, we require:

Healthy egg and sperm

The egg and sperm provide the genetic blueprint for development. Each embryo needs a complete set of 46 chromosomes – 23 from the egg and 23 from the sperm. Some embryos inherit incorrect genetic instructions that can impact embryo development and make it harder for them to divide and grow as expected.

Mitochondrial energy

Embryos need energy to divide and grow, which is provided by mitochondria (tiny energy-producing structures in cells). Poor mitochondrial function can slow or stop embryo development.

Efficient metabolic function

An embryo’s metabolic function provides both energy and the building blocks needed for development. This includes the creation of protein and fats, and the removal of waste products that can be toxic to the embryo. Together, these provide what the embryo needs for growth, cell division and viability.

Timely cell division

Embryos should ideally divide at a regular pace (2-cell, 4-cell, 8-cell, etc.). Uneven and/or delayed division can mean the embryo is of suboptimal quality and may not develop as expected.

Embryonic genome activation

Around Day 3 (see diagram below), embryos start using their own DNA instead of relying on maternal DNA (genetic code from the egg). If this DNA transfer is inadequate, interrupted or missing, this can slow or stop the development of an embryo.

Stable conditions

Embryos need the right temperature, oxygen and pH balance to grow. These factors are carefully assessed and monitored continuously in the laboratory environment.

Difficulties or inaccuracies in any of these processes can affect the way an embryo grows and can impact whether an embryo will reach the blastocyst stage (where it has divided into many cells), making it suitable for transfer or freezing.

Safeguarding your embryos is our highest priority

We understand how important every embryo is to your journey. That’s why we use the most advanced technology and scientifically proven methods to create the ideal environment for embryo development. From carefully performing every procedure to closely monitoring each embryo’s progress, our highly trained embryologists work tirelessly to give each embryo the best possible chance to grow and thrive.

We maintain strict laboratory conditions, including precise temperature, humidity and air quality control to mimic the natural environment as closely as possible. Our team carefully observes each embryo’s development at every stage. Even though not all embryos will reach the blastocyst stage, please know that we do everything in our power to maximise their potential. Your dream of building a family is at the heart of everything we do, and we are committed to providing the best possible care every step of the way.

If you have any questions about embryo development or your fertility journey, please reach out to Newlife IVF. In the meantime, let’s walk through the different stages of embryo development to help you better understand the process.


Building resilience during IVF – how to cope with the highs and lows

Building emotional resilience during IVF treatment can help you manage these emotions, recover from setbacks and cope with life’s difficulties and uncertainties.

What is resilience?

‘Resilience is the process of adapting well in the face of adversity, trauma, tragedy, threats or significant sources of stress.’1

Being resilient does not mean avoiding feelings of stress or emotional pain – rather, it is adapting to difficult or unexpected circumstances and bouncing back from the experience.

Resilience improves your wellbeing during fertility treatment

Concerning fertility, research has shown that higher levels of resilience among couples struggling with fertility are associated with enhanced quality of life and emotional stability, as well as lower fertility-related distress.2
Beyond helping you cope during fertility treatment, building resilience can have a positive impact on your overall health and wellbeing, leading to3:

    • Fewer depressive symptoms
    • Improved adaptation to stress
    • Enhanced ability to cope during distressing experiences
    • Improved physical health.


How to build resilience during fertility treatment

Like progressively strengthening a muscle, you can learn to become more resilient to life’s challenges over time. Here are some examples that may help.

Grow supportive connections

Drawing on the support of those around you, including your partner (where applicable), family or friends, can help share the emotional load of your experience as you continue with your fertility treatment.4 Help is a two-way street – in addition to accepting help, supporting your loved ones through difficult moments can help you feel connected to others while giving you a sense of satisfaction, in turn strengthening your resilience. Small and simple gestures like checking in with a friend or lending an empathetic ear while others are dealing with stress can also distract you from an inward focus where you feel stuck in your own problems.

Manage uncertainty

During fertility counselling sessions, we often dive into how to navigate feelings of uncertainty and lack of control that can be experienced during fertility treatment. This is because learning how to accept uncertainty – not just during fertility treatment but throughout life in general – can help develop resilience.

But merely accepting the unpredictability and ‘unknowns’ of your fertility care is not an easy thing to do, which is why we recommend practising mindfulness. Instead of latching onto feelings of uncertainty when these thoughts arise, acknowledge their existence and try to move through these feelings. This is one of the hardest things to do, so be kind to yourself while you work on this.

Set small, achievable goals

The pride and sense of accomplishment you feel when achieving a goal is motivating and energising, helping you to feel more optimistic. Research has shown that breaking down your overarching goal into smaller short-term goals can help reframe your mindset while also relieving feelings of disappointment after a negative fertility treatment cycle.4

So ensuring that your goals are achievable is a great way to build resilience. In this instance, the importance is not the goal itself but the process of setting small goals and noticing your progress.

Break down each step in your fertility treatment cycle into mini-goals – this might include taking your hormone injections each day, completing your blood tests and scans, having your embryo transfer or intrauterine insemination procedure, or getting through each day of the two-week wait before finding out whether the treatment resulted in the outcome you were hoping for.

Sprinkle in some joy

There can be moments of sadness and loss when trying to conceive, which can make it harder to appreciate other joys in life, particularly if your fertility journey is regularly on your mind (as it’s very easy for treatment to become a sole focus).

Try to maintain some ‘normality’ in your life by engaging in activities that bring you joy.4 Humour is also effective in helping to develop a more resilient nature, so exploring activities that make you laugh while giving you a break from treatment can help you stay connected to day-to-day life.

Take the time to reflect

Think back on obstacles that you have previously overcome and recognise that you have already been developing resilience over the years, perhaps without knowing it. Reflect on past situations that have caused you stress, grief or trauma and ask yourself:

      • What worked in helping you to cope during these times?
      • What didn’t work well?
      • Who were the best people to help you at those times?

Take these learnings about building resilience during your IVF journey and draw on them when working through any disappointing or unexpected outcomes.

Connect with our supportive counselling team

Our compassionate Newlife IVF counsellors are here to guide you through every step of your journey.

At Newlife IVF, we are committed to supporting our patients the best we can, which includes providing you with additional counselling sessions at no extra cost. To book an appointment with one of our counsellors, call (03) 8080 8933 or email us at [email protected]. And to make things easy for you, we are more than happy to consult with you over the phone so you don’t have to take time off work.

Remember, you have made it through rough times before. You’ve got this.

References


  1. American Psychological Association. Building your resilience. American Psychological Association. 2020. Accessed 20249. https://www.apa.org/topics/resilience ↩
  2. Herrmann D, Scherg H, Verres R et al. Resilience in infertile couples acts as a protective factor against infertility-specific distress and impaired quality of life. J Assist Reprod Genet. 2011;28(11):1111–1117. doi:10.1007/s10815-011-9637-2 ↩
  3. Quyen G, Vandelanotte C, Cope K, et al. The association of resilience with depression, anxiety, stress and physical activity during the COVID-19 pandemic. BMC Public Health. 2022;22. ↩
  4. Bailey A, Ellis-Caird H, Croft C. Living through unsuccessful conception attempts: a grounded theory of resilience among women undergoing fertility treatment. J Reprod Infant Psychol. 2017 Sep;35(4),324–333. https://doi.org/10.1080/02646838.2017.1320366 ↩ ↩ ↩

Newlife IVF recognised for excellence again

Based on figures published by the Herald Sun, sourced from the Federal Government’s Your IVF Success website, Newlife IVF recorded the highest pregnancy rates in Victorian patients under 35 years (per treatment cycle attempt in 2024), achieving a 52% pregnancy success rate (compared with the national average of 41%). Exceptional outcomes were also achieved across older age groups, with pregnancy success rates of 43% for women aged 35–38 years (the national average is 35%) and 31% for women aged 39–42 years (the national average is 25%).

Newlife IVF also excelled in live birth rates across Victoria, achieving an outstanding result of 52% for patients under 35 years (46% is the national average), and 27% for 35–42 year olds (the national average is 24%).1 Notably, since its establishment nearly seven years ago, Newlife IVF has consistently delivered outcomes that surpass the national average.

‘We’re proud of what these results mean for our patients, with pregnancy and birth outcomes that continue to exceed the national average,’ said Dr Nicole Hope, fertility specialist and Medical Director at Newlife IVF. ‘Our approach is built on precision and care at every stage. Our specialists focus on optimising conditions for egg quality and embryo development and implantation, while our embryologists bring exceptional attention to the care of eggs, sperm and embryos. Alongside this, our wider team – including nurses, counsellors, genetic counsellors and administrative staff – provides dedicated support across the many aspects of fertility care that influence wellbeing and outcomes. Together, this depth of expertise creates a strong foundation for patient success.’

Outstanding success rates backed by best-practice patient care

Results like these are not achieved by chance. They reflect a clear and consistent philosophy that has guided Newlife IVF since its inception.

Newlife IVF was built on a shared vision to do things differently. From the beginning, the goal was to create a fertility clinic that puts patients before profits, combining best-practice science with genuinely personalised care and support. Every decision and every advancement have been guided by that principle.

As a clinician-owned and led fertility clinic, Newlife IVF is proud to be an independent specialist fertility centre. This independence enables a more supportive and patient-focused experience than is often possible within large corporate-owned clinics.

‘Our results are a reflection of how we work as a connected team,’ said Dr Tiki Osianlis, Managing Director and Scientific Director at Newlife IVF. ‘Clinical expertise and best scientific practice are essential, but they are only part of the picture. What truly sets our care apart is the way our team collaborates around each patient. We take the time to listen, to understand their circumstances, and to adapt treatment accordingly. That shared commitment across every role allows us to deliver care that is both highly individualised and deeply supportive as patients work towards building their family.’

A patient-first approach to fertility care

Every aspect of care at Newlife IVF is designed with patients in mind. From our state-of-the-art laboratory to the use of advanced scientific tools and techniques, expert-led care is combined with cutting-edge technology to maximise each patient’s chance of success.

At Newlife IVF, we believe everyone deserves the opportunity to build their family. That belief underpins our commitment to making high-quality fertility treatment as accessible as possible. We remain focused on delivering outstanding results alongside compassionate, personalised care, supporting our patients every step of the way as they work towards building the family they dream of.

Appointments with one of our fertility specialists in Melbourne are available for those ready to explore their next steps. Call us on (03) 8080 8933 or book an appointment online.

Footnotes


  1. These measures represent the births per completed egg retrieval cycle. Success rates are based on the number of live births that resulted from the eggs collected from women in 2022 that were fertilised and implanted as embryos in 2022 and 2023. Source: YourIVFsuccess. ↩